JBRA Assisted Reproduction 2025;29(Suppl.2 SBRA 2025):74
29th Annual Congress of the SBRA. São Paulo/SP - Brazil, 2025
doi: 10.5935/1518-0557.20263653
P-62. Does endometrial thickness predict chemical pregnancy in frozen embryo transfer? Analysis of 522 artificial cycles performed by a single physician
JBRA Assisted Reproduction 2025;29(Suppl.2 SBRA 2025):74
Poster Presentation
29th Annual Congress of the SBRA. São Paulo/SP - Brazil, 2025
doi: 10.5935/1518-0557.20263653
P-62. Does endometrial thickness predict chemical pregnancy in frozen embryo transfer? Analysis of 522 artificial cycles performed by a single physician
1 Universidade Federal de Goias - Goiânia - GO – Brasil
2 Humana Medicina Reprodutiva - Goiânia - GO - Brasil
Objective: The aim of this study is to evaluate whether endometrial thickness is associated with pregnancy rates in women undergoing frozen embryo transfer (FET) following artificial endometrial preparation cycles.
Methods: This is a retrospective study, using last author medical records of patients who underwent a frozen-thawed embryo transfer (FET) cycle from January 2021 to December 2024. All patients were monitored and transferred by the same physician, received the same endometrial preparation and underwent FET at the blastocyst stage. On the day of transfer, transvaginal ultrasound examination was performed to evaluate endometrial thickness (ET). The pregnancy was confirmed by β-hCG test (> 25mIU/ml) about two weeks after the transfer. Statistical analysis was performed using Mann-Whitney, regression analyze, ROC curve and chi square test (x2 ), p≤0.05.
Results: Between 2021 and 2024, a total of 522 frozen embryo transfers (ET) were performed with pregnancy rate 71.68%; 44 patients were excluded: one because the embryo did not survive, sixteen embryos were transferred at the cleavage stage and twenty-seven for confounding variable, resulting in a final sample of 478 patients. The chemical pregnancy rate (PR), after the exclusion criteria, was 70.29%. The median age of these participants was 34.9 years (range, 23–49). After stratification by group the median age was 34.64 years in Group A and 35.30 years in Group B. Endometrial thickness (ET) in the patients included in the study ranged from 3.6 to 20 mm, with a median of 8.25 mm and mean 8.82. Following group stratification, the median endometrial thickness was 8.2mm in Group A and 8.45mm in Group B and no statistically significant difference was observed between the groups. Linear regression analysis demonstrated a non-significant inverse association between endometrial thickness and pregnancy rate (r=-2050; 95% CI: -3.914 to 1.504; p=0.3182), indicating that endometrial thickness was not a statistically significant predictor of pregnancy. To assess the endometrial thickness cutoff, a ROC curve analysis was performed with an area under the curve (AUC)=0.55 and sensitivity and specificity values of 0.542 and 0.518, respectively. Based on the ROC analysis, an optimal cut-off value of 8.3 mm was identified and patients were subsequently stratified into two groups: Group 1 with endometrial thickness ≤ 8.3 mm and Group 2 with endometrial thickness > 8.3 mm. No statistically significant difference in pregnancy rates was observed between the groups (p=0.4944) as shown in Table 1. Considering scientific evidence that supports 7 mm as the minimum threshold for optimal endometrial receptivity, a chi-square test was performed to compare pregnancy rates between two groups stratified by endometrial thickness: < 7 mm and ≥ 7 mm. In this study, no statistically significant difference in pregnancy rates was observed between these groups (p=0.1036).
Conclusion: In the present study, endometrial thickness was not identified as a significant predictor of pregnancy, even when ET was ≤7 mm—commonly considered ‘thin' in the literature. Furthermore, pregnancy rates did not differ significantly when comparing two distinct cutoff values, suggesting that the routine practice of canceling embryo transfers based solely on endometrial thickness may be clinically unwarranted.
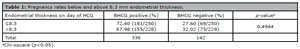
Table 1. Pregnancy rates below and above 8.3 mm endometrial thickness.
aChi-square (p<0.05).